UHC Provider Portal Log In: Truth About Claim Denials
Every revenue cycle manager and medical biller knows the daily routine: you launch your browser, enter your One Healthcare ID, and complete your United Healthcare provider portal log in: the shocking TRUTH about claim denials, however, is that the explanation posted on your screen rarely tells the complete story. While the portal dashboard may summarize a rejection in a clean, sanitized phrase like “Service Not Covered” or “Non-Covered Charges,” the underlying mechanisms driving these determinations are far more complex, automated, and aggressively engineered than most practices realize.

Understanding what happens behind the scenes of the UnitedHealthcare (UHC) claims engine is essential for protecting your practice’s bottom line. When thousands of dollars in clean claims turn into unpaid accounts receivable, navigating the portal effectively is the difference between recovering revenue and writing off legitimate care.
The Illusion of the Portal Dashboard
The modern UHC provider portal (hosted via UHCprovider.com) was designed to centralize administration, offering digital claims submission, eligibility checks, and prior authorization workflows. Yet, the high-level rejection messages visible on the front-end interface often obscure the exact operational or clinical rules triggered in the back-end adjudicator.
When billing staff review a rejected line item, they frequently encounter high-level Claim Adjustment Reason Codes (CARCs) that point toward administrative technicalities. In reality, modern payer adjudication relies heavily on predictive algorithms, automated policy bundling edits, and cross-system logic checks that search for discrepancies across patient demographic files, national provider databases, and National Correct Coding Initiative (NCCI) tables before human eyes ever see the documentation.
United Healthcare Provider Portal Log In: The Shocking TRUTH About Claim Denials
The most eye-opening aspect of modern health plan adjudication is the sheer volume of claims denied without manual clinical review. Payers process hundreds of millions of claims annually; manual review of each record is operationally impossible. As a result, UHC relies heavily on sophisticated algorithmic filters and automated rules engines.
1. Algorithmic Downcoding and Automated Edits
One of the most pervasive drivers of revenue loss is automated downcoding, particularly on Evaluation and Management (E/M) services. Algorithms evaluate your practice’s historical billing patterns against geographic specialty benchmarks. If your distribution of high-complexity codes (such as 99214 or 99215) exceeds statistical averages, claims may be systematically flagged or automatically reduced to lower levels of service, citing lack of documented medical necessity.
2. The Prior Authorization Disconnect
Practices frequently secure an authorization number, verify it as active, bill the approved CPT codes, and still receive an immediate denial upon portal lookup. Why? The automated system checks for microscopic mismatches between the authorization shell and the final claim line:
- The rendering provider’s individual NPI versus the group billing NPI.
- A place-of-service code differing between the initial request (e.g., POS 11 for office) and the billed claim (e.g., POS 22 for outpatient hospital).
- Unlisted or add-on codes billed alongside the primary approved code that were not explicitly included in the initial determination.
3. Artificial Coordination of Benefits (COB) Roadblocks
Another systemic driver of zero-dollar remittances is the automated COB update flag. UHC’s engine routinely flags commercial and Medicare Advantage claims with a denial stating the patient has other primary insurance, even when the patient has had sole coverage through UHC for years. Until the subscriber calls member services to verbally confirm no secondary policy exists, the portal will systematically block payment on all submitted claims.

How to Uncover the Root Cause Inside the Portal
Relying solely on the main claims status screen will leave your billing team running in circles. To find the actionable truth behind a denial, billers must extract secondary data layers nested within the portal architecture.
- Inspect the Electronic Remittance Advice (835 ERA): Do not rely exclusively on the web summary. Download the raw remittance or review the detailed Remittance Advice Remark Codes (RARCs). Codes like M15 (“Separately billed services not covered”) or N382 (“Missing/incomplete/invalid clinical documentation”) offer precise targets that the summary screen omits.
- Check the Document Vault: Automated letters outlining specific medical necessity guidelines or audit determinations are automatically routed to the Document Vault. Many billing teams miss critical appeal deadlines simply because they monitored the claim status grid rather than checking the correspondence repository.
- Cross-Reference Clinical Policy Bulletins: UHC updates its medical and drug policies monthly. When a denial references “experimental/investigational” or “benefit limitation,” search the portal’s Clinical and Radiology Policy directory for the specific CPT code to review exact diagnostic criteria required for reimbursement.
Step-by-Step Strategy to Overturn Denials on UHCprovider.com
Once you have diagnosed the actual mechanism of denial, you must choose the correct administrative path. Submitting an appeal when a reconsideration is required—or vice versa—resets the adjudication clock and can lead to timely filing expirations.
Reconsideration vs. Formal Appeal
UHC distinguishes strictly between these two paths:
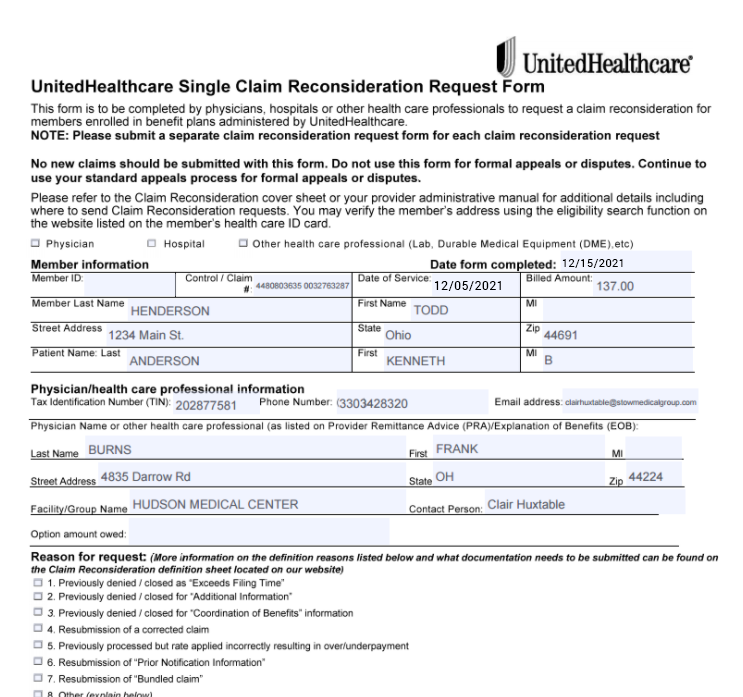
- Claim Reconsideration: Used for technical, coding, or payment disputes (e.g., incorrect modifier application, mistaken demographic mismatch, or missing initial attachment). This should be submitted directly via the portal’s “Claims & Payments” tool within 12 months of the initial adjudication.
- Formal Appeal: Required when an adverse clinical determination has been made (e.g., denial based on medical necessity, experimental treatment exclusions, or authorization refusal). This requires comprehensive medical records, a physician narrative, and targeted citations from peer-reviewed literature or UHC’s published policy.
Optimizing Document Attachments
When uploading records through the portal’s Document Submission interface, avoid the temptation to dump the entire electronic medical record (EMR). Automated intake systems convert uploads to black-and-white optical character recognition (OCR) files. If key details are buried in 80 pages of laboratory flowsheets, the reviewer will often uphold the denial.
Instead, create a targeted packet: lead with a one-page cover letter referencing the Claim Number, Member ID, Date of Service, and specific CPT codes in dispute. Highlight the specific sections of the clinical notes that satisfy UHC’s policy prerequisites, such as failed conservative therapies or explicit diagnostic scores.
Proactive Measures to Protect Your Practice Revenue
Fighting denials after the fact is costly, averaging between $25 and $118 per appealed claim in administrative labor. To minimize portal intervention, implement upstream safeguards:
- Run Strict Pre-Encounter Eligibility: Verify coverage within 48 to 72 hours of scheduled appointments using real-time EDI 270/271 transactions to catch COB and termination flags before treatment begins.
- Scrub Unbundled Modifiers: Review claims carrying Modifiers 25, 59, and the X{EPSU} series. Ensure documentation clearly substantiates an entirely distinct, separately identifiable service performed during the same encounter.
- Leverage the “Track It” Tool: Assign an administrative lead to audit UHC’s “Track It” worklists twice weekly. This feature centralizes active reconsiderations, missing info requests, and prior authorization tasks, preventing claims from slipping past contractual appeal windows.
The UnitedHealthcare provider portal is a powerful operational tool, but it rewards precision and proactive management. By understanding the underlying logic of automated adjudication, looking past surface-level denial codes, and methodically leveraging digital appeals, practices can reclaim lost revenue and streamline their overall billing cycle.